
Investigating How Physical Work Limits AI Substitution across Medical Specialties
Investigating How Physical Work Limits AI Substitution across Medical Specialties
As artificial intelligence weaves itself into health care, it may have big implications for physician work. Needing to physically interact with the patient is likely to affect how different specialties are affected by AI.

Artificial intelligence can already read scans, draft diagnoses and talk with patients, so there is much speculation in the health-care community on whether AI may soon replace physicians.
But software can’t examine bodies, perform surgeries or biopsies, so the amount of hands-on work in a specialty sets a limit on how much AI algorithms could substitute for tasks physicians perform in those fields.
To measure that limit, Dan Zeltzer, PhD, at UC Berkeley—together with Stanford Health Policy’s Maria Polyakova, PhD, Victoria Udalova, PhD, at the U.S. Census Bureau, and Stanford students Tyler Tam and Benji Bhattacharya—sorted nearly $45 billion in 2023 Medicare payments to 590,000 physicians in 56 specialties by whether each service requires physical contact.
Their results, published in a NEJM AI Perspective, reveal sharp variation in the share of physical services—which AI can’t substitute at this point—across medical specialties. Fields such as dermatology and orthopedic surgery have a high share of services in which patients are typically treated with hands and instruments, rather than by examination, diagnosis or prescription. Across all specialties, only about a fifth of all Medicare payments go to services with no physical barrier to AI’s role. On average, the longer a specialty’s training, the greater its physical share of services.
In fields like family medicine, internal medicine, and emergency medicine, the likely impact of AI is the most uncertain. In these specialties, the most common tasks physicians perform involve evaluation and management of patients. This sometimes involves both physical exams and work that ranges from routine care to complex diagnostics. The degree to which AI can substitute for this work is uncertain. The catch is that some of these specialties are among the ones with the most shortages: AI could replace some of that work and support other parts, and its future impact on alleviating shortages will thus depend on how clinical AI tools are designed and implemented.
“The fields most accessible as career paths and most needed to relieve primary care shortages thus face the greatest uncertainty, because AI could impact their work as either a substitute or a complement—an outcome shaped as much by how AI is designed, deployed, and reimbursed as by the technology itself,” said Polyakova, an associate professor of health policy at Stanford.
In a chart that sorts the 15 largest specialties by revenue, researchers estimated how much of specialties’ Medicare payments involve hands-on, physical interaction with patients. They found that the top hands-on specialties include dermatology, which bills 68% of its revenue for physical procedures; orthopedic surgery 53%; ophthalmology 45%. Only 7 to 13% of their work is the kind that software has the potential to substitute for. On the other end, the services diagnostic radiology bill Medicare for consist almost entirely of tasks that do not require an in-person physical interaction with the patient.
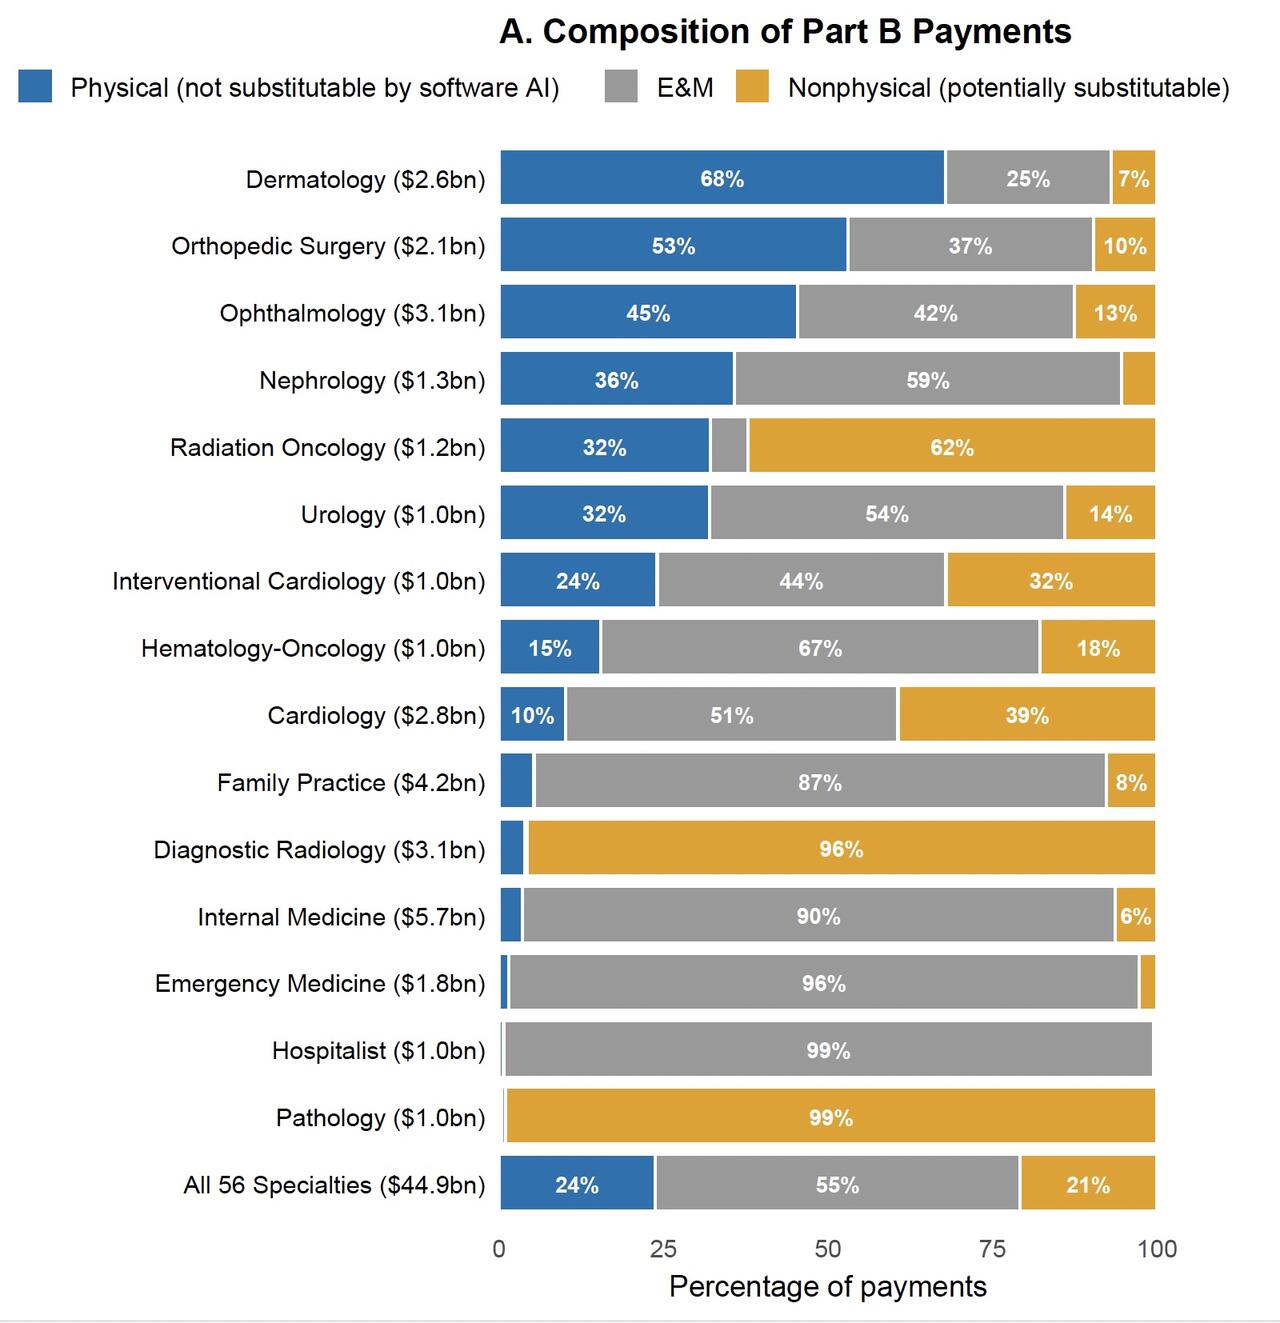
Substitution of physician work by AI is more plausible in radiology and other specialties where work is done by interpretation and not by touch. Conversely, surgeons and proceduralists are largely shielded from AI substituting for their tasks. The study notes that AI could still, however, augment and assist physical procedures, as it already does, for example, by flagging polyps in real time in colonoscopies. And in the future, robotics and hardware-integrated systems may, over time, weaken the barrier to substitution in procedural fields. AI may end up augmenting physician work in every specialty.
Lead author Zeltzer, however, notes: “The fact that a task is non-physical does not immediately mean it is replaceable—that would depend on how good AI algorithms become, and there may still be a long way before we trust AI with such work.”
Further, the researchers believe that substituting for non-physical tasks doesn’t mean physicians will no longer be needed, although the composition and nature of their work may change, shifting effort to physical procedures, relational aspects, and other tasks where human skills are essential and irreplaceable.
The key takeaway is that across all 56 specialties analyzed, 24% of Medicare physician payments go to hands-on work that AI algorithms can’t touch today, 21% to work with no physical barrier to AI, and 55% to visits that involve an uncertain mix of physical and non-physical work. Yet these shares vary a lot by specialty, so the shape of AI in medicine will depend a lot on the mix of tasks different specialists do, and how it is developed to meet these tasks.


